
4 years old male child came to OPD with fever for 12 days ,cough for 6 days ,and difficulty in breathing for last 24 hours.
On examination respiratory distress was present with deep inspiratory crackles over right mammary region
The child was admitted in hospital and treatment started with IVF,antibiotic and oxygen by nasal prongs as the Spo2 breathing room air was 90%
On exploring the history further, child had suffered from 3 episodes of Pneumonia in past 3 years, repeated episodes of otitis media being treated by ENT Specialists ,2 episodes of sinusitis and 3 episodes of Diarrhoea
On detailed clinical examination after stabilisation,it was noticed that lymph nodes were not palpable in cervical region and tonsils were not noticeable on throat examination
The child was faltering on growth
On the basis of it ,we suspected Primary Immune Deficiency most likely,X-linked Agammaglobulinemia/Brutons Agammaglobulinemia and started investigations on this line
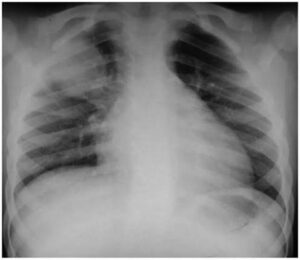
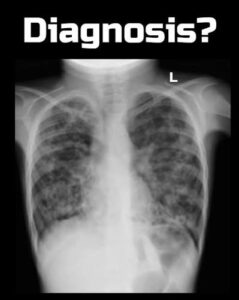
On chest X-Ray this time, there was consolidation right upper lobe and middle lobe looking like round Pneumonia, previous multiple Chest radiographs was showing consolidation and air bronchogram
Blood picture was suggesting bacterial infection and blood was sent for flow cytometry along with Immunoglobulin level
The child did not respond to one antibiotic in 72 hours and the antibiotic was escalated and after 96 hours the child started to show some response .We continued the antibiotic and the child became afebrile after about 1o days of second antibiotic.
Culutre of BAL fluid after Bronchoscopy showed H.influenzae & Moraxella catarralis
,sensitive to Linezolid and Meropenam
Immunoglobulin profile showed very low levels of IgG,IgM,Ig E & IgA
Flow cytometry report came which revealed markedly low percentage of B-Lymphocytes with normal T lymphocytes
Genetic study was sought which confirmed the diagnosis by showing mutation in BTK gene which is consistent with X-linked Agammaglobulinemia
Case Discussion:
In a child suffering from repeated episodes of sinusitis,otitis media,pneumonia with faltering growth,Primary Immune Deficiency should be kept as one diagnostic possibility.Other diagnosis which may be possible is Primary Ciliary Dyskinesia-PCD or CF-Cystic Fibrosis
In case of a child who is growing normally with no serious infection in first 6 months of life and suffering thereafter with repeated sinopulmonary infections and repeated otitis media , X-linked agammaglobulinemia should be suspected in male child who also started faltering in growth after 6 months of life.
X-linked agammaglobulinemia is X-linked recessive disorder seen in male child. For the initial 6 months, due to the presence of maternal IgG passed in baby through placenta, there is less chance of severe bacterial infection in children. After that period,as the maternal IgG level decreases,the infection fighting capacity of the child decreases because there is no B cell to produce antibody in children with mutation in BTK gene. There is arrest of B cell production at the level of pro B cell.
There may be Bronchiectasis duue to repeated lung infections and persistence of infections in these children.
Bronchiectasis itself becomes a cause of repeated lung infections in these children
Lymph nosdes may be absent along with absence of tonsils and adenoid in theses children due to absence of lymphoid proliferation
In some children small lymph nodes, small tonsils and small adenoid may be found due to activation of T -Lymphocytes
Screening
Male Infants with family history of XLA in the maternal uncle should be screened for XLA
Diagnosis
In suspected cases markedly reduced Serum IgA,IgM,IgG,IgE
Flow cytometry-Less than 1-2% B Lymphocytes(CD 19/CD20 Cells) ,T Lymphocytes -normal
Deficieny of Bruton tyrosine kinase
Genetic study- Mutation in BTK gene -confirms the diagnosis
Treatment
Aggressive treatment of lung infections should be done with adequate dose and duration of antibiotics.
Early recognition and early treatment may prevent the development of Bronchiectasis which develops in late treated and inadequately treated infections in children
Mainstay treatment is IVIG 400-500 mg per kg at an interval of 3-4 weeks or when trough level reaches with prompt treatment of infections
Complication
Bronchiectasis
PRECAUTION
Live vaccines specially oral polio vaccine should be avoided
For more knowledge of Pediatric Pulmonology-Join Fellowship Program in Pediatrc Pulmonology with Bronchoscopy & Sleep Study under aegis of Respiratory Foundation of India
Click here to apply for the course-https://respifoundation.com
Faculty-Dr.Deo Kumar Jha
Alumnus of AIIMS New Delhi
Recipient of Dr APJ Abdul Kalam Azad Health Award 2026 for Excellence in Pediatric Pulmonology,Bronchoscopy,Intensive Care & Sleep Study
Featured in Forbes India
References
- Kanegane H, Tanita K, Nishimura M, et al. Revisiting X-linked agammaglobulinemia. Journal of Human Immunity. 2025;1(1):e20250020. doi:10.70962/jhi.20250020.
- Conley ME, Notarangelo LD, Etzioni A. X-linked agammaglobulinemia. Clinical Immunology. 1999;93(3):185–192. doi:10.1006/clim.1999.4779.
- Winkelstein JA, Marino MC, Lederman HM, et al. X-linked agammaglobulinemia: report on a United States registry of 201 patients. Medicine (Baltimore). 2006;85(4):193–202. doi:10.1097/01.md.0000229482.27398.5c.

