
8 years old male child who was a diagnosed case of asthma and well controlled on controller therapy came to emergency with complaint of fever for 3-4 days ,cough for 3 days and chest pain for 2 days.Chest pain was on left side of chest which was aggravated during inspiration.On exploring the history. child was having less appetite for about 2-3 weeks and lost significant weight during this period
On clinical examination ,there was mild dehydration,high respiratory rate of 38 breaths per minute ,high pulse rate of 160 beats per minute and temperature of 101° F (38.3° C),BP-104/72 mm of Hg
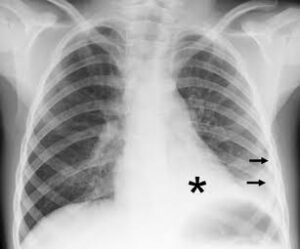
On chest examination, movement was less on the left side of chest,percussion note was dull over left side of chest on inframammary region,and on auscultation there was no bronchial breath sound , intensity of breath sound was diminished over the same region with inspiratory crackles
Chest X-Ray was done which revealed left sided pleural effusion
Pleural fluid exmination was showing hemorrhagic pleural fluid, with 90% lymphocytes,total cell count 1504/ml, gram staining was negative and LDH was 1700 U/L
CBC was done which was within the normal limit but ESR was high-80 mm in first hour
In plural fluid final report-malignant cells were detected
Flow cytometry and immunocytochemistry of pleural fluid confirmed the diagnosis of Non Hodgkin’s Lymphoma-NHL
Case discussion
Pleural effusion is most commonly seen as a complication of pneumonia in children,called parapneumonic effusion
When in doubt ,means, if it is not as a complication of Pneumonia,pleural fluid tapping and examination is done.
Light’s criteria is applied to differentiate between transudative and exudative pleural effusion
According to this criteria ,if any one of the following is present 1.the ratio of pleural fluid protein to serum protein is more than 0.5, 2. the ratio of pleural fluid LDH to serum LDH is > 0.6 and 3. the level of pleural fluid LDH is more than 2/3 rd of the upper limit of level serum LDH, it is exudative
If the collection of pleural fluid is rapid or recurrent and associated with profound weight loss with systemic symptoms,malignant pleural effusion should be suspected and worked up accordingly
In children, the most common cause of malignant pleural effusion if non Hodgkin’s lymphoma
In NHL pleural effusion-the pleural fluid is exudative ,with lymphocyte predominant,it may be hemorrhagic and sometimes chylous.Total cell count in the pleural fluid may not be high and LDH is raised
Other causes of lymphocytic predominant pleural effusion are-Tuberculosis, Sarcoidosis, Rheumatoid arthritis,Cronic lung infection
Pathophysiology of malignant pleural effusion-
There are two ways-Direct invasion of lymphatics by malignant cells and indirect through increased permeability of capillaries in presence of malignant cells causing local inflammatory changes
Clinical Presentation
Usual clinical presentation is with fever,weakness,breathing difficulty,weight loss,malaise and chest pain.
Unusually it may present with low grade fever and cough
Suspect in a child with anterior mediastinal mass, respiratory distress, swelling of face and neck or venous congestion
Diagnosis
1.It is diagnosed by detecting malignant cells in pleural fluid.Sometimes biopsy and histopathological examination is required.
2. Flowcytometry
3.Immunohistochemistry
Clinical critical caution –a child with large anterior mediastinal mass can develop immediate catastrophic airway compromise with collapse when placed supine, sedated or put under general anesthesia
For more knowledge in Pediatric Pulmonology,Bronchoscopy, Intensive care and Sleep Medicine
Join Fellowship in Pediatric Pulmonology with Bronchoscopy and Sleep Study under Respiratory Foundation of India
Faculty- Dr.Dev Kumar Jha/Dr.D.K.Jha
Recipient of Dr.APJ Abdul Kalam Azad Health Award 2026,for Excellence in Pediatric Pulmonology, Bronchoscopy,Intensive Care and Sleep Medicine
Alumnus of AIIMS,New Delhi
Click here to apply-https://respifoundation.com
WhatsApp 9899186848
REFERENCES:
- Arnold DT, De Fonseka D, Perry S, Morley A, Harvey JE, Medford A, Brett M, Maskell NA. Investigating unilateral pleural effusions: the role of cytology. The European respiratory journal. 2018 Nov:52(5):. pii: 1801254. doi: 10.1183/13993003.01254-2018. Epub 2018 Nov 8 [PubMed PMID: 30262573]
-
Feller-Kopman DJ, Reddy CB, DeCamp MM, Diekemper RL, Gould MK, Henry T, Iyer NP, Lee YCG, Lewis SZ, Maskell NA, Rahman NM, Sterman DH, Wahidi MM, Balekian AA. Management of Malignant Pleural Effusions. An Official ATS/STS/STR Clinical Practice Guideline. American journal of respiratory and critical care medicine. 2018 Oct 1:198(7):839-849. doi: 10.1164/rccm.201807-1415ST. Epub [PubMed PMID: 30272503]

