
14 years female came to OPD with complaint of shortness of breath for 4 days, blood in sputum for 3 days ,fever for 12 days,cough for 14 days
On clinical examination she was febrile, with RR 20 Breaths per minute,PR-100 per minute, Blood Pressure 120/70 mmHg
On chest examination ,movement was decreased on left side ,percussion note was dull and on auscultation,air entry diminished over the left lung
Chest X-Ray was showing Pleural effusion on left side with ill defined opacities bilateral lung fields.
Pleural fluid examination confirmed a chylus pleural effusion
On exploring the history further,parents said the same happened 4 months back and X-Rays carried by parents were showing two times pneumothorax
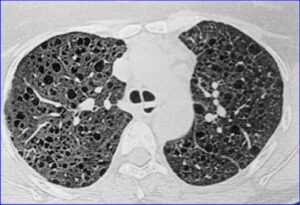
HRCT Chest was done which showed bilateral multiple cystic lesions
Serum VEGF-D was done ,the level of which was 1200pg/ml
The Diagnosis was confirmed as Lymphangioleiomyomatosis-LAM
Case discussion
LAM is rarely seen in children and almost exclusively seen in young and adolescent girls or adult women
It is caused by abnormal proliferation of smooth muscle cells around airways,blood vessels and lymphatics
It has strong association with genetic mutation of TSC 1 and TSC 2 activating TSC-mTOR pathway
There may be features of Tuberous Sclerosis
Clinically it presents as cough, breathlessness,wheeze ,fever is usually due to secondary infection,recurrent pneumothorax,recurrent chylus pleural effusion, Hemoptysis,may be recurrent chylus ascites.
CBC is within normal range
PFT shows obstructive pattern and DLCO may reduce
Serum VEGF-D-Vascular endothelial growth factor D is raised and a level more than 800 pg/ml is strong;y suggestive of LAM
Diagnosis is made in presence of clinical feature,Raised serum VEGF-D and HRCT Chest showing bilateral thin walled cystic lesions of almost equal sizes
Lung biopsy is not required but if done the immunohistochemistry shows HMB 45 POSITIVE, alpha SAM positive cells and Melan A positive cells–LAM cells
These three if present is highly characteristic of LAM
Differential Diagnosis-Langerhans cell histiocytosis-LCH,Cystic Fibrosis,Lypmphocytic interstitial Pneumonitis,congenital cystic lung malformation-CPAM
Treatment -Long term, for years,oral Sirolimus in the dose of 0.1 mg per kg once daily for children and 2 mg daily for adults with monitoring of trough level
References:
Chang WY, Cane JL, Blakey JD, Kumaran M, Pointon KS, Johnson SR. Clinical utility of diagnostic guidelines and putative biomarkers in lymphangioleiomyomatosis. Respiratory research. 2012 Apr 18:13(1):34. doi: 10.1186/1465-9921-13-34. Epub 2012 Apr 18 [PubMed PMID: 22513045]
Hagaman JT, Schauer DP, McCormack FX, Kinder BW. Screening for lymphangioleiomyomatosis by high-resolution computed tomography in young, nonsmoking women presenting with spontaneous pneumothorax is cost-effective. American journal of respiratory and critical care medicine. 2010 Jun 15:181(12):1376-82. doi: 10.1164/rccm.200910-1553OC. Epub 2010 Feb 18 [PubMed PMID: 20167846]
To learn Pediatric Pulmonology-Join Fellowship Program in Pediatric Pulmonology with Bronchoscopy and Sleep Study under aegis of Respiratoty Foundation of India
Click here to join-https://respifoundation.com
WhatsApp-9899186848
Faculty-Dr Dev Kumar Jha
Alumnus of AIIMS,New Delhi
Recipient of Dr.APJ Abdul Kalam Azad Health Award 2026 for Excellence in Pediatric Pulmonology,Bronchoscopy,Intensive care and Sleep Study
Featured in Forbes India

